
CLINICAL EVIDENCE

The image is used for illustrative purposes only and does not represent an actual patient.
AT 5 YEARS, HEMGENIX® DEMONSTRATED SUSTAINED DURABILITY AND EFFICACY1,2
HEMGENIX® is the first approved gene therapy for haemophilia B in the UK.1,3
HEMGENIX® HOPE-B STUDY DESIGN
The HOPE-B study was designed to evaluate the efficacy and safety of HEMGENIX® in adults with severe or moderately severe haemophilia B.4
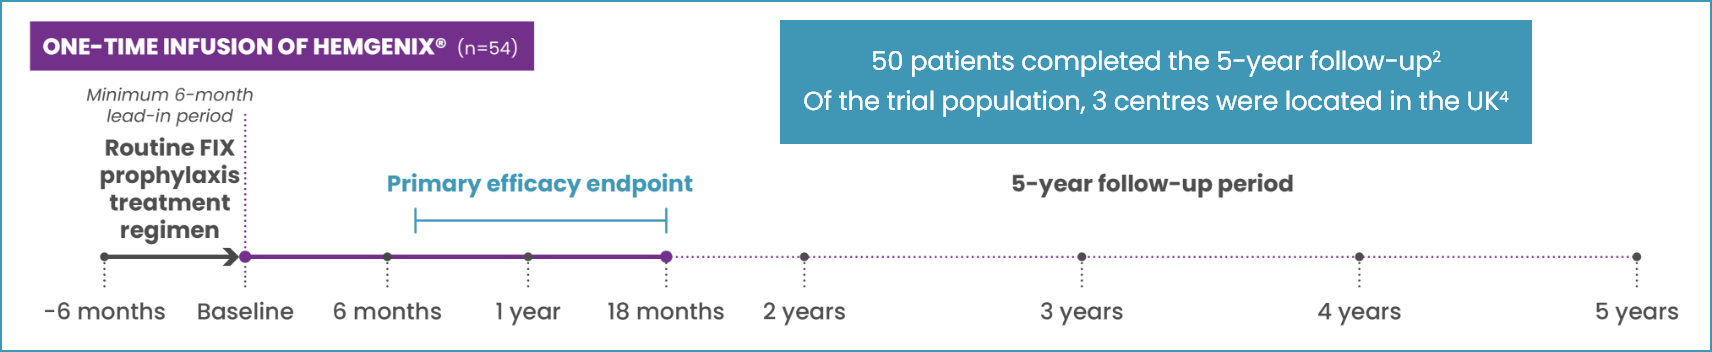


PRIMARY ENDPOINT:4
Comparing annualised bleeding rate (ABR) for all bleeds for non-inferiority between prophylaxis in the 6-month lead-in period and the 52 weeks following stable FIX expression (months 7–18) post-dosing of HEMGENIX®
KEY SECONDARY ENDPOINTS:4
- FIX activity at 6, 12, and 18 months after dosing
- Proportion of patients remaining free of continuous prophylaxis
- Occurrence and resolution of target joints, and proportion of patients with zero bleeds
- Correlation of FIX activity levels to pre-existing AAV5 NAb titre
- Patient-reported outcome scores on the International Physical Activity Questionnaire (iPAQ) and the EuroQol 5-Dimension 5-Level (EQ-5D-5L) Questionnaire

KEY INCLUSION CRITERIA4
Male; ≥18 years of age; has congenital haemophilia B (FIX activity ≤2% of normal); currently on continuous FIX prophylaxis for ≥2 months prior to screening

KEY EXCLUSION CRITERIA2
- History of FIX inhibitors
- Positive FIX inhibitor test at screening and Visit L-Final
- Values of >2 x ULN for selected laboratory tests at screening
- Positive HIV test (not controlled with antiviral therapy)
- Active hepatitis B or C infection
- Evidence of liver fibrosis
- Previous gene therapy treatment
Efficacy
Primary endpoint: Comparing ABR for all bleeds for non-inferiority between prophylaxis in the 6-month lead-in period and the 52 weeks following stable FIX expression (months 7–18) post-dosing of HEMGENIX®.4
SUPERIOR BLEED PROTECTION AT 7–18 MONTHS VERSUS LEAD-IN FIX PROPHYLAXIS*1,4
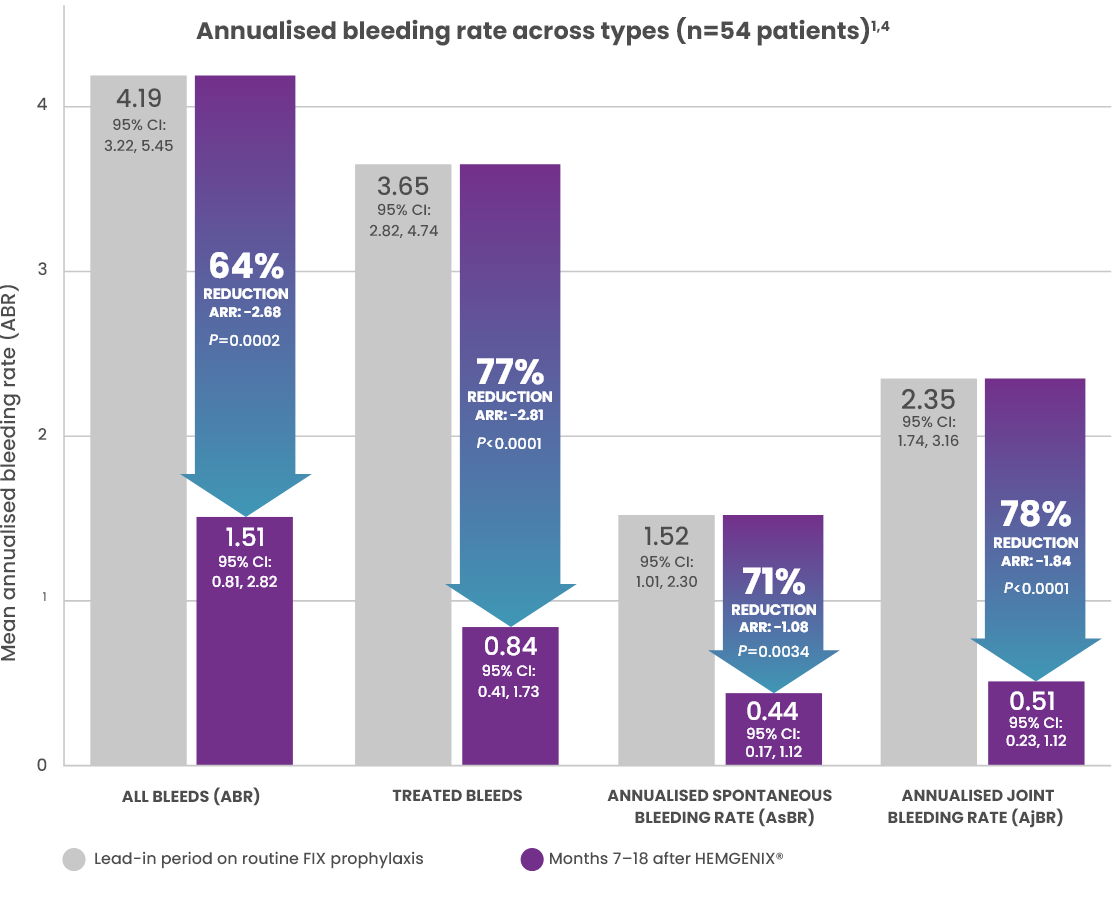
63% of patients (34/54) reported zero bleeds† in the 7–18 month period following a one-time infusion of HEMGENIX®, which decreased to 37.0% of patients (20/54) at 60 months.5
This graph includes the full analysis set (FAS) of 54 patients for the 7-18 month period. The FAS included 1 patient who received only 10% of the planned dose and 1 patient who did not respond to treatment (pre-existing AAV5 NAb titre of 1:3212).4
*The ABR for all bleeding episodes decreased following treatment from a rate of 4.19 (95% CI: 3.22, 5.45) during lead-in to 1.51 (95% CI: 0.81, 2.82) post-treatment. The observed ABR ratio post-treatment vs. lead-in was 0.36 (95% Wald CI: 0.20, 0.64). Since the upper bound (0.64) is both lower than the non-inferiority margin of 1.8, and lower than 1, both non-inferiority and superiority (secondary endpoint) vs. control group during lead-in was declared. One-sided P values, not adjusted for multiplicity.1,4
†All types of bleeds: spontaneous; traumatic; FIX treated or not.
Pre-specified 5-year analyses included adjusted ABR (difference between months 7–60 after gene therapy versus lead-in period), FIX expression and safety outcomes.2
SUPERIOR BLEED PROTECTION AT MONTH 60 VERSUS 6-MONTH LEAD-IN FIX PROPHYLAXIS2,5
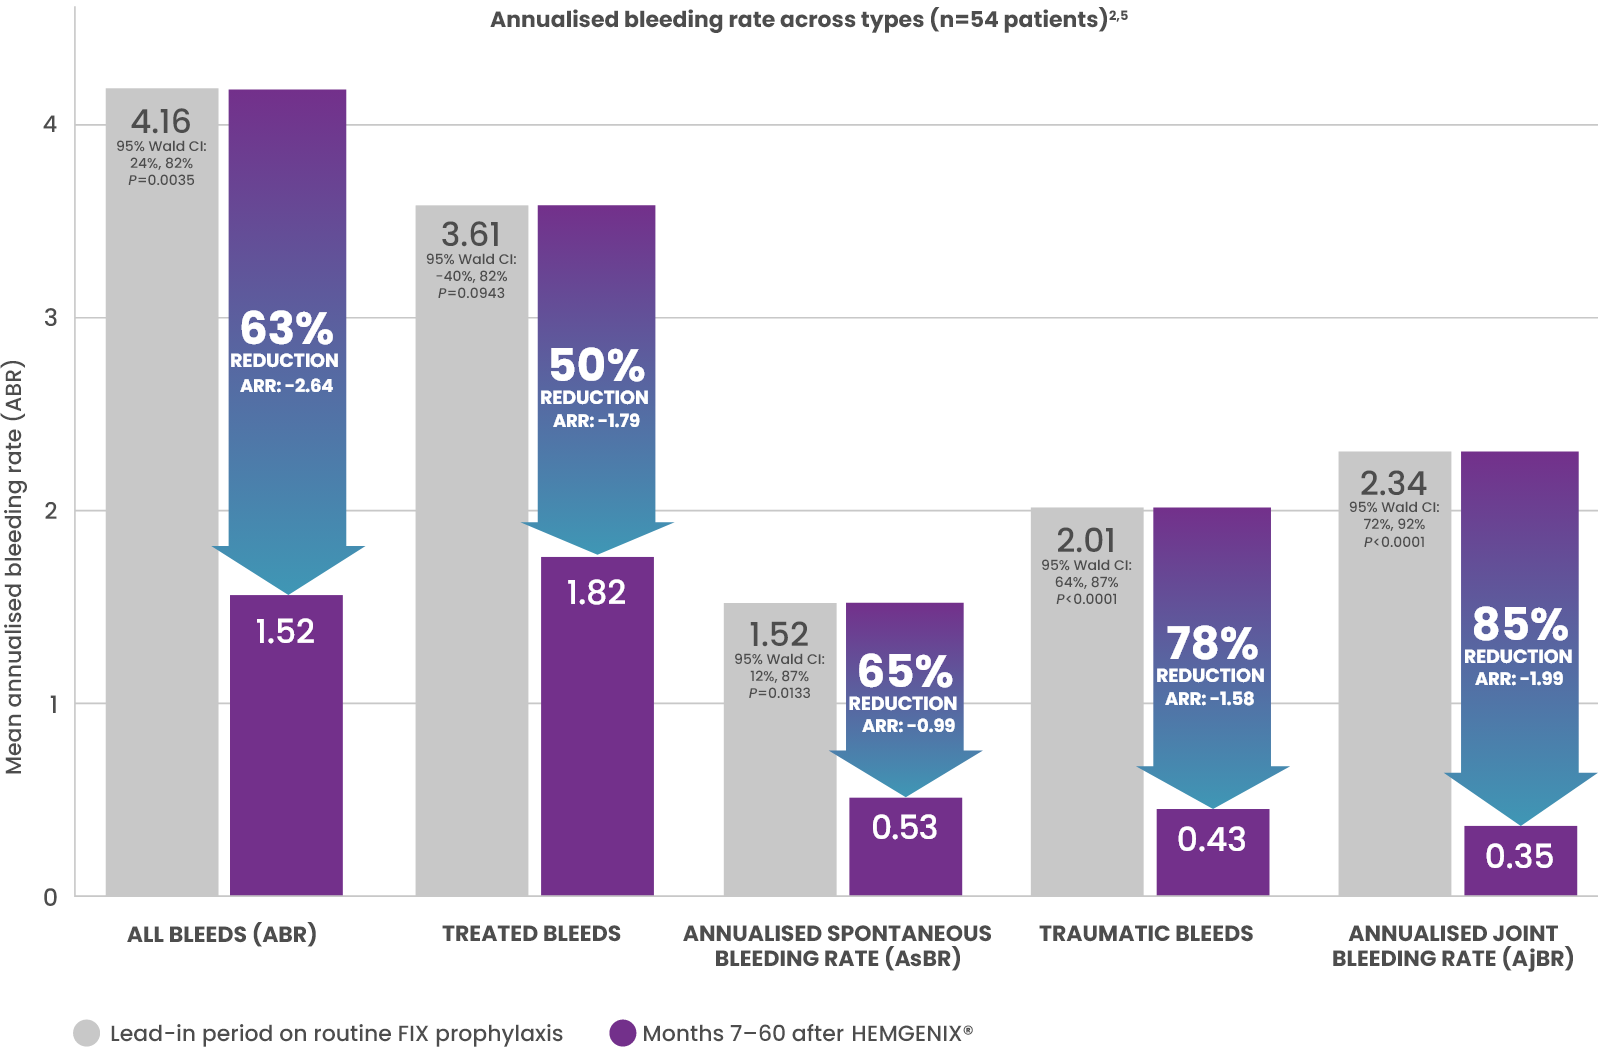
~63% REDUCTION IN ABR SEEN AT 18 MONTHS WAS SUSTAINED FOR 5 YEARS versus stable prophylaxis in 6-month lead-in period (1.52 vs. 4.16; ARR: -2.64 bleeds; P=0.0035).*1,2
This graph includes the full analysis set (FAS) of 54 patients for the 7–60 month period.2,5
*Mean ABR for all bleeds during months 7-60 post-treatment was significantly reduced by 63% (mean ABR 1.52) compared with the ≥6-month lead-in period (mean ABR 4.16; P=0.0035). Total number of bleeds (all types) was 136 during the ≥6-month lead-in period and decreased to 55 during year 1, 48 during year 2, 37 during year 3, 22 during year 4, and 19 during year 5 post-treatment.2
Secondary endpoint: Proportion of patients remaining free of continuous prophylaxis.4
MAJORITY OF PATIENTS REMAINED FREE OF PROPHYLAXIS AT 5 YEARS WITH HEMGENIX®2
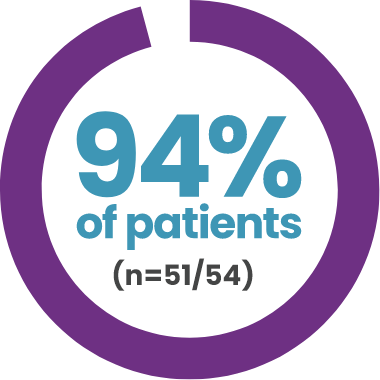
DISCONTINUED ROUTINE FIX PROPHYLAXIS
and remained prophylaxis free at 5 years2
- 2 participants had no FIX expression. Between months 24–60, 1 patient returned to continuous regular FIX prophylaxis and 1 patient did not respond to treatment (pre-existing AAV5 NAb titre of 1:3212)
- No participants resumed prophylaxis between months 37–60

IN OVERALL MEAN ANNUALISED FIX CONSUMPTION
over 5 years post-treatment compared to the ≥6-month lead-in period (P<0.0001)*2
*52/54 (96.3%) patients remained free of continuous regular FIX prophylaxis from day 21 to month 24 post-treatment. 1 participant eventually had his FIX levels decline to <5%; his bleeding phenotype returned and he resumed prophylaxis at month 29 post-treatment.2
AAV5, adeno-associated viral vector serotype 5; ABR, annualised bleeding rate; AjBR, annualised joint bleeding rate; AR, absolute reduction; AsBR, annualised spontaneous bleeding rate; ARR, absolute risk reduction; CI, confidence interval; EQ-5D-5L, EuroQol 5-Dimension 5-Level; FAS, full analysis set; FIX, Factor IX; Haem-A-QoL, Haemophilia Quality of Life Questionnaire for Adults; HIV, human immunodeficiency virus; iPAQ, Physical Activity Questionnaire; NAb, neutralising antibody.
Factor IX levels
Secondary endpoint: FIX activity at 6, 12 and 18 months after dosing.4
Pre-specified 5-year analyses included adjusted ABR (difference between months 7–60 after gene therapy versus lead-in period), FIX expression and safety outcomes.2
ELEVATED AND SUSTAINED FIX LEVELS FOR 5 YEARS AFTER HEMGENIX® INFUSION1,2,4,5
FIX activity was sustained over 5 years after dosing2,5
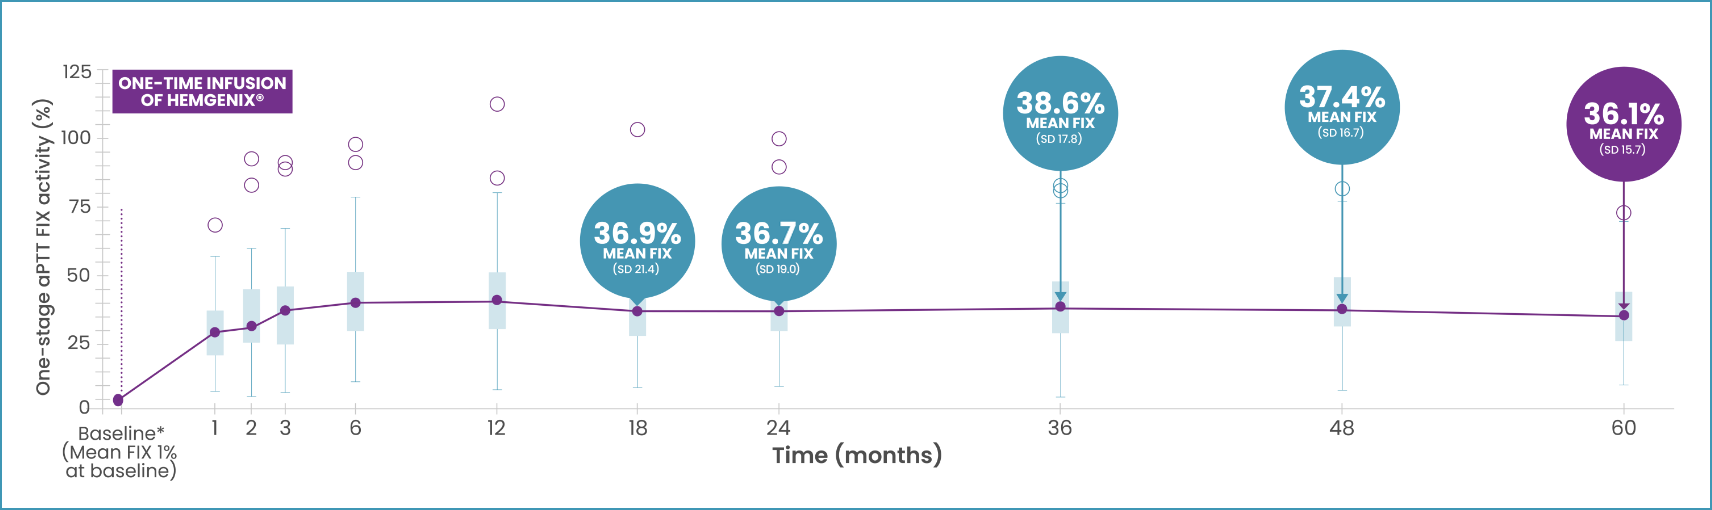

No clinically meaningful correlation was identified between a subject’s AAV5 NAb titre at baseline (up to a titre of 1:700) and their FIX activity at month 36 post-dose.2
O data outliers.
*Baseline FIX was imputed based on the subject’s historical haemophilia B severity documented on the Case Report Form. If the subject had documented severe FIX deficiency (FIX plasma level <1%), their baseline FIX activity level was imputed as 1%. If the subject had documented moderately severe FIX deficiency (FIX plasma level ≥1% and ≤2%), their baseline FIX activity level was imputed as 2%.4
This graph includes the full analysis set (FAS) of 54 patients. The FAS included 1 patient who received only 10% of the planned dose and 1 patient who did not respond to treatment (pre-existing AAV5 NAb titre of 1:3212).2
AAV5, adeno-associated viral vector serotype 5; ABR, annualised bleeding rate; FAS, full analysis set; FIX, Factor IX; NAb, neutralising antibody; SD, standard deviation.
Quality of life
Secondary endpoint: Patient-reported outcome scores on the iPAQ and the EQ-5D-5L Questionnaire.5
PATIENTS' OVERALL QUALITY OF LIFE5
There were no significant differences observed in the iPAQ total physical activity scores between lead-in period and month 12 after treatment. At month 12, the Haem-A-QoL score decreased compared with the lead-in period.4
5-year follow-up analysis
Recorded in the domains of feelings, treatment, work/school, and future up to month 60 (P<0.005) post-treatment compared with the ≥6-month lead-in period, using the Haem-A-QoL score.5
There were significant improvements observed in the EQ-5D-5L scores between months 12–24 post-treatment compared to the ≥6-month lead-in period (P=0.0244).5
EQ-5D-5L, EuroQol 5-Dimension 5-Level; FIX, Factor IX; Haem-A-QoL, Haemophilia Quality of Life Questionnaire for Adults; iPAQ, Physical Activity Questionnaire.
Safety Profile
AT 5 YEARS, THERE WERE NO SERIOUS ADVERSE EVENTS RELATED TO TREATMENT WITH HEMGENIX®2
At 60 months post-dose, 39/54 (72.2%) participants experienced at least 1 TRAE2
Almost all TRAEs occurred during the first 6 months (91%)2
The most common TRAEs* at 60 months post-treatment were:†2
- Headache: 14.8%
- ALT increased: 18.6%
- Influenza-like illness: 13%
- AST increased: 11.2%
- CPK increased: 7.4%
- Dizziness: 7.4%
- Fatigue: 7.4%
- Nausea: 7.4%
IRR occurred in 3 (6%) participants2
No SAEs reported were considered TRAEs2
SAEs reported that were determined to be unrelated to treatment included:2
- Glossopharyngeal schwannoma
- Myelodysplastic syndrome
- HCC
- Hypertensive urgency
- 1 death caused by cardiac amyloidosis
- 1 death related to cardiogenic shock
*TRAEs reported in >5% of participants.2 TRAEs were defined as adverse events considered by the investigator as possibly related or related to treatment.2
†Adverse events were categorised according to preferred terms of the MedDRA, version 24.1.2
ALT, alanine aminotransferase; AST, aspartate aminotransferase; CPK, creatine phosphokinase; HCC, hepatocellular carcinoma; IRR, infusion-related reaction; MedDRA, Medical Dictionary for Regulatory Activities; SAE, serious adverse event; TRAE, treatment-related adverse event.
Important safety considerations
SPECIAL WARNINGS & PRECAUTIONS
CONTRAINDICATIONS1
- Hypersensitivity, active infections, and patients with known advanced hepatic fibrosis, or cirrhosis.
Initiation of treatment1
- Need to assess for pre-existing AAV5 antibodies, evaluate the patient’s liver transaminases, and perform liver ultrasound and elastography, alongside laboratory tests to evaluate for active hepatitis B and C.
- In patients with active hepatitis B or C, treatment must be postponed until the infection is no longer active.
Monitoring1
- Patients should be monitored during the infusion and at least 3 hours after. Patients require monitoring regularly after treatment for FIX activity and transaminases. If ALT is raised, consider corticosteroid taper. Also recommended to perform regular abdominal ultrasound and monitor for AFP elevations during at least 5 years.
Thromboembolic events1
- Patients with pre-existing risk factors may be at higher risk.
Risk of Malignancy1
- The clinical relevance of individual integration events is not known to date, but it is acknowledged that individual integration into the human genome could potentially contribute to a risk of malignancy. In the clinical studies, no malignancies were identified in relation to treatment with HEMGENIX®
Contraception1
- Contraceptive measures are required for male patients or their female partners of childbearing potential.*
Donations1
- Patients must not donate semen, blood, organs, tissues, and cells.
Immunocompromised patients or those with active/controlled infections were not included in clinical studies.1
For full safety information, including special warnings and precautions for use, and full monitoring requirements, please refer to the Summary of Product Characteristics before prescribing.
*For 12 months after administration of HEMGENIX®.1
AAV5, adeno-associated viral vector serotype 5; AFP, alpha fetoprotein; ALT, alanine aminotransferase; FIX, Factor IX.
References
1. HEMGENIX® (etranacogene dezaparvovec). Summary of product characteristics. 2. Pipe SW et al. Final Analysis of a Study of Etranacogene Dezaparvovec for Hemophilia B. N Engl J Med. 2026;394(5):463–474. 3. Pipe S et al. Long-Term Bleeding Protection, Sustained FIX Activity, Reduction of FIX Consumption and Safety of Hemophilia B Gene Therapy: Results from the HOPE-B Trial 3 Years after Administration of a Single Dose of Etranacogene Dezaparvovec in Adult Patients with Severe or Moderately Severe Hemophilia B. Blood. 2023;142(Suppl 1):1055. 4. Pipe SW et al. Gene Therapy with Etranacogene Dezaparvovec for Hemophilia B. N Engl J Med. 2023;388(8):706–718. 5. Data on file: Study CSL222_3001 (HOPE-B): Final 5-year follow-up analysis. Database Extract Date: 30 April 2025.
Adverse Event Reporting
▼This medicine is subject to additional monitoring. Adverse events should be reported. Reporting forms and information can be found at www.mhra.gov.uk/yellowcard or search for MHRA Yellow Card in the Google Play or Apple store. Adverse events should also be reported to CSL Behring UK Ltd on 01444 447405 or medinfo@cslbehring.com.
